Pain is both a sign and a stress factor. In emergency care, it likewise comes to be a threat variable: unrelieved pain drives tachycardia, raises blood pressure, clouds assessment, and can complicate transportation and treatments. Brief training courses in pain monitoring, aligned to PUAEME008 Offer pain management, exist to produce confident frontline experts that can analyze, make a decision, and supply risk-free analgesia within their extent. Obtaining that right takes more than a pharmacology lecture. It requires scenario-based judgment, knowledge with regional protocols, and a self-displined strategy to paperwork and client safety.
I have actually educated, investigated, and freshened multiple programs that claim to "give pain management training." The programs that really transform practice tend to share a few top qualities. They connect drug choices to specific client presentations, they pierce the operational details that fail under pressure, and they level about compromises. They likewise map thoroughly to PUAEME008 so that students can gain an acknowledged pain monitoring certificate, not just a certification of attendance.
This post lays out what PUAEME008 requires in method, how brief courses suffering monitoring can satisfy the standard, and how to choose the right pain administration program for your duty, whether you are a registered nurse in immediate care, a paramedic, a physio therapist handling acute flare-ups, or a clinician upskilling for remote location work.
What PUAEME008 In fact Covers
PUAEME008 Supply pain management rests within public safety and security training, and it supports pain alleviation to risk-free systems of treatment. The system focuses on temporary, procedural, and sharp pain in prehospital and emergency contexts, not lasting persistent discomfort. Crucial element include:
- Accurate analysis utilizing validated pain scales appropriate to age and cognitive status, and duplicated reassessment after interventions. Selection and administration of analgesia within organisational plans, commonly including inhaled methoxyflurane, oral anesthetics, intranasal fentanyl, or morphine depending upon jurisdiction and scope. Monitoring, adverse event preparedness, and rise, consisting of administration of queasiness, hypotension, respiratory system clinical depression, and transformed sensorium. Documentation that captures standard, treatment, action, and handover detail, and interaction with receiving teams. Scene and bystander safety and security, permission, and culturally suitable care.
While the specific medication checklist varies by solution, the PUAEME008 provide pain monitoring framework is medication agnostic. It is about safe systems: evaluate, determine, supply, keep an eye on, file, and turn over. Any kind of reliable give pain administration course that claims to meet PUAEME008 should make those steps noticeable in every scenario.
Why short programs benefit busy clinicians
Time stress is an actual constraint. Dedicating to a multi-day program is tough for change employees. Brief programs in pain monitoring, normally six to ten hours with combined online and face-to-face components, use a sensible course to pain administration qualification without endangering clinical changes. When well designed, a certification course hurting monitoring can deliver concentrated abilities that translate to area performance the exact same night.
Speed, however, can not come at the cost of deepness. The best discomfort management training programs equilibrium crisp pre-read material with immersive, hands-on practice. If you can complete a course without ever before managing a spacer, setting up a methoxyflurane tool, or preparing an intranasal dose, it is not likely to build functional skills.
The core abilities a PUAEME008-aligned program must produce
Every discomfort administration certificate training course straightened to PUAEME008 must demonstrably build the following expertises:
Pain analysis that endures the sound. A single numeric ranking is not nearly enough. Learners must utilize age-appropriate tools like Wong-Baker faces for youngsters, Behavioural Discomfort Range surrogates in the overwhelmed individual, and simple concerns that punctured the adrenaline of trauma scenes. Reliable courses show you to triangulate: the person's record, their practices and physiology, and your mechanism-of-injury intuition.
Safe medicine choice within extent. Medication menus vary. Country nurses might have authority for intranasal fentanyl and dental analgesics, while event paramedics may rely on methoxyflurane alone. Students have to practice decision trees that mirror their real protocols. As an example, a sickly client with a broken neck of femur, nil by mouth, hypotensive at 92/58 and SpO2 95 percent on space air will not tolerate the very same plan as a young hill bicycle rider with a mid-shaft shin crack and stable vitals.
Dose computation under pressure. Intranasal fentanyl in micograms per kilogram, optimum per nostril volume, redosing intervals, and advancing totals are where errors creep in. Great training utilizes drills with simulated syringes and atomisers, and pressures you to recite your 5 legal rights out loud. Watching someone fumble a dose throughout simulation tells me more than any kind of created test.
Adverse result readiness. Antiemetics for methoxyflurane-induced queasiness, naloxone protocols for opioid-induced breathing anxiety, additional oxygen, and placing methods require to be automated. A training course that never mimics a decrease in respiratory system rate after fentanyl misses out on the point.
Reassessment and documentation. Discomfort alleviation is a process, not a one-off act. Students must chart standard pain, time of administration, dose, course, result at five and 10 mins, and any side effects. That paperwork ends up being a handover shorthand that secures the client and the clinician.
Medication choices in range for PUAEME008
Because policies differ by state and service, a discomfort administration qualification course usually presents a conventional tool kit with neighborhood changes. The common choices:
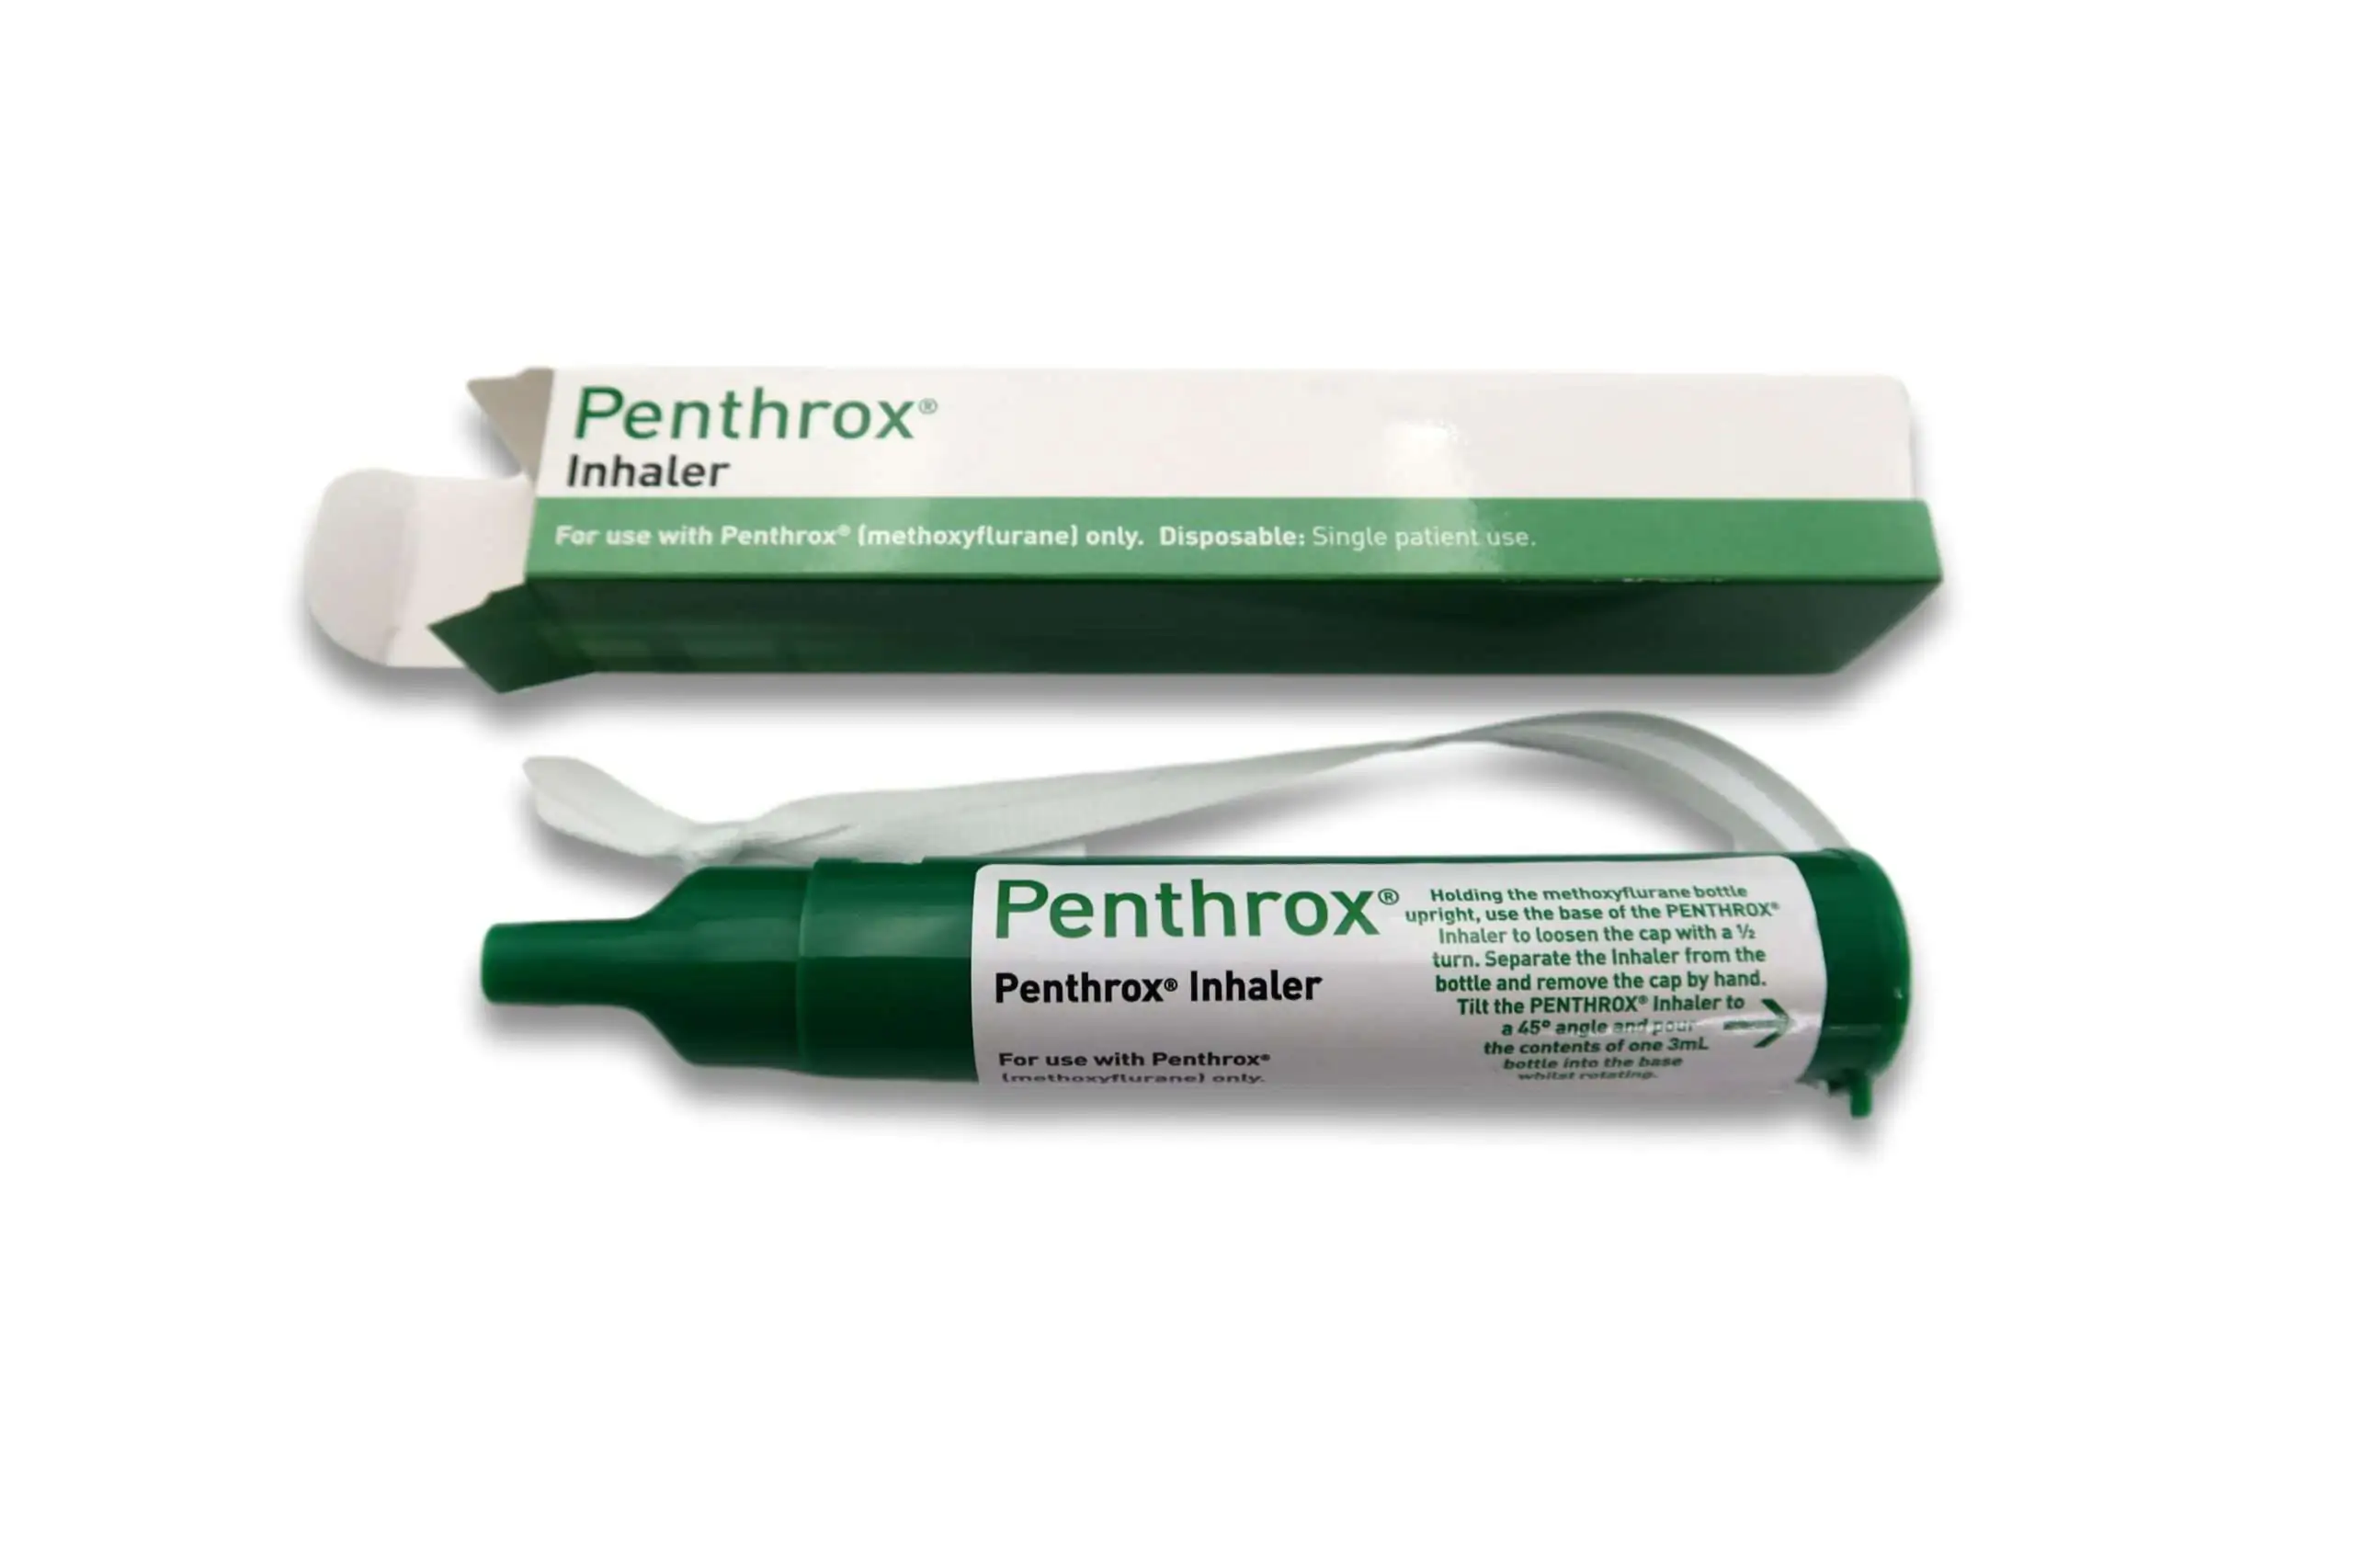
Methoxyflurane. A mobile breathed in analgesic used commonly in prehospital treatment. It provides fast onset and patient-controlled application. Drawbacks include lightheadedness and nausea, and it is not suitable for extended use or in clients with certain renal threat profiles. In crowded scenes, coaching the individual to breathe in and breathe out away from onlookers matters greater than the majority of learners anticipate. A two-minute coaching session can make or damage its effectiveness.
Intranasal fentanyl. Rapid start, needle-free, and very easy to titrate. It is outstanding for cracks and burns, and helps with anxious children. Find more information The dose-volume limitation for the nostrils is a genuine restraint. If you fill up the nose beyond concerning 1 millilitre complete volume, it trickles as opposed to atomises, which blunts impact and increases danger. Individuals discover this just by exercising with atomisers and enjoying the spray pattern.

Oral analgesics. Paracetamol and NSAIDs stay the backbone of multimodal analgesia. In the field, they are complements that lower opioid requirements. The course needs to educate when dental agents help and when they only include delay, such as the nil-by-mouth trauma individual awaiting surgery.
Morphine or IV opioids. In some solutions, PUAEME008 students will certainly not give IV opioids; in others, they will under guidance. If IV courses are consisted of, cannulation abilities are thought preexisting, and the program must concentrate on titration, monitoring, and documentation as opposed to cannulation itself.
Adjuncts and regional blocks. A lot of brief programs do not train nerve blocks within PUAEME008, yet some solutions use intranasal ketamine or nitrous mixes under different protocols. If a training course promotes ketamine without extended monitoring content, ask questions.
A legitimate pain administration training carrier will publish the specific medication range for their PUAEME008 supply pain management course and cross-reference to neighborhood methods. Obscure pledges regarding "effective medications" are a red flag.
Building confidence through circumstance realism
The classroom can overemphasise clean lighting and best hearing. Actual scenes rarely comply. I once watched a new graduate lose control of a crack splint because he attempted to maintain sterility in a sloppy paddock while the patient howled. The veteran close to him, silently, protected standard comfort first: a blanket as a splint reinforce, a fast analgesic dosage, and afterwards a secure move to firmer ground. No person keeps in mind the discomfort range number from that telephone call, yet everybody keeps in mind that the client stopped clawing at the leg after the initial inhalations.
Effective short training courses suffering management stage these details intentionally. They utilize history sound, a cramped area, or an anxious relative who maintains disrupting. They make you clarify to a parent why you are providing an analgesic to a youngster with a shed before you begin cooling, or just how you will certainly time oral paracetamol prior to a long rural transportation. The factor is not to trick students yet to inoculate them versus typical failure settings: inadequate interaction, reluctance, and loss of sequence.
Documentation that withstands scrutiny
Charts and handovers are commonly the starting point auditors look. A pain administration certificate should come with much better paperwork practices. A strong discomfort monitoring course for nurses, paramedics, and initial responders drills concise expressions that record medical thinking. Instead of "gave fentanyl," compose "IN fentanyl 60 mcg at 14:12 for L lower arm crack, pain 8/10 to 4/10 at 14:18, no queasiness, RR 16 stable, SpO2 98 percent." That line can be skimmed and trusted. It is also defensible months later on when memory fades.
Handing over to the obtaining team, call out the analgesia sequence with doses and times, any kind of issues with methoxyflurane resistance, last oral medication time, and whether the client remains zero by mouth. If your service allows a second line agent, state whether you considered it and why you kept back. Excellent programs make that specific in debrief.
Tailoring to different professional roles
The material alignment varies when you teach pain management training courses for nurses versus discomfort management courses for physiotherapists.
For nurses in immediate care or remote facilities, discomfort administration training for nurses frequently emphasises triage acceleration, standing orders, and paperwork under nurse-led versions. The curriculum ought to include double-check systems when functioning solo, dispensing regulations, and communication with on-call medical policemans. Situations need to entail completing top priorities, as an example a perturbed patient with kidney colic arriving while a dressing modification is underway.
For physiotherapists that run into severe flare-ups, a discomfort monitoring qualification program has to respect range. The training course might focus on screening warnings, immediate non-pharmacologic methods, easy dental analgesia advice where allowed, and safe reference. Educating a physio to coach paced breathing or to position a back radiculopathy client for comfort issues more than medicine drills. Discomfort management training courses for physio therapists that meddle innovative anesthetics without a clear scope declaration can mislead learners.
For event paramedics and first responders, PUAEME008 give discomfort management usually restricts medicines to inhaled and oral courses. Scene monitoring, client positioning before transport, and handling spectator assumptions become core abilities. The course ought to include crowd-communication manuscripts, since they decrease conflict when you carry out analgesia in public view.
Non-pharmacologic methods that really help
Medications are not enough, especially when transportation is postponed or doses are constrained. An all-round discomfort administration training course incorporates strategies that reduce experiencing without a milligram being given.
Positioning remains the peaceful hero. A client with a proximal humerus fracture that is resting screw upright will strain and safeguard. A straightforward sling and pillow, with the seat delicately reclined, can halve the discomfort score prior to the initial breathing. Show trainees to check for pressure factors and change assistances. In burns, altitude and gentle cooling while maintaining core warmth issue; overcooling extends transport and boosts discomfort.
Communication is analgesia. Patients who recognize what takes place following usually relax sufficient to endure the very early mins. A short manuscript aids: "I am mosting likely to offer you something you take a breath that soothes within a min. Maintain it secured versus your mouth and Great post to read breathe in deeply three times. You manage just how much you take, and you can stop if you really feel lightheaded. I will certainly stick with you and check your numbers." Programs need to need students to state those words aloud while establishing the device.
Immobilisation and splinting provide mechanical relief. Training has to consist of improvised options for when kits run completely dry: rolled towels, triangular plasters, a folded up magazine for a wrist. Perfection is the enemy of alleviation. Pair splinting experiment instant analgesic mentoring to show how the two job together.
Breathing techniques are not just for antenatal courses. Mentoring sluggish nasal breathing with a longer breathe out minimizes sympathetic drive. When teamed with intranasal fentanyl, the technique often steadies the client enough to avoid hyperventilation or breath-holding that delays atomiser delivery.
Edge instances where judgment matters
No course can manuscript every situation, however a PUAEME008-aligned program should emerge predicaments that compel trade-offs.
The drunk trauma person. Alcohol complicates opioid use and masks discomfort. A stiff guideline of "no opioids with alcohol" leaves individuals wincing, however laid-back application risks respiratory clinical depression. Effective training shows mindful titration with enhanced monitoring, choice for breathed in agents if available, and an emphasis on respiratory tract positioning and transport readiness.
The frail older grown-up with numerous comorbidities. Age adjustments pharmacodynamics. A small intranasal dosage can generate big effects, and methoxyflurane queasiness can cause desire threat. An excellent trainer makes students rehearse half-doses, slower titration, and early antiemetic consideration. The balance between comfort and safety and security becomes a discussion with the client and carer.
The youngster that refuses to breathe in. Forcing a tool to the face backfires. Courses ought to educate the alternate path within range or show rise actions, consisting of topical anaesthetic for IV if permitted, distraction strategies, or a short delay while a caretaker models first smokes. Role-playing this with a hesitant teacher functioning as the youngster deserves more than any slide.
The long transport in a hot rescue. Methoxyflurane sheds effectiveness with tool cooling and leaks. Intranasal agents might dry nasal mucosa. Preparation a staggered dosage pattern, making sure hydration where risk-free, and building in keeping an eye on breaks becomes part of the situation. Learners must be asked to plan analgesia for a 90-minute rural roadway, not just a suv 10-minute sprint.
Assessment, reassessment, and when to escalate
Pain monitoring is dynamic. The initial strategy may underperform. Training courses that press students to reassess and pivot construct safe reflexes. If inhaled analgesia provides only minimal relief, do not keep chasing the exact same impact out of habit. Consider a second technique if range allows, or couple with non-pharmacologic adjustments. If a client's discomfort aggravates or transforms personality, treat that as brand-new information: reassess for area syndrome threat, developing stomach pathology, or a missed injury.
Know your rise limits. Respiratory price dropping below a service-defined floor, SpO2 falling in spite of oxygen, new confusion, or unrestrained vomiting all trigger details responses. Students have to have those numbers and activities at their fingertips. In programs I run, I need trainees to verbalise a rise line, for instance, "If RR dips below 10 or the person comes to be rousable to voice just, I will certainly discontinue opioids, support the air passage, and prepare naloxone per procedure."
Evidence base without the jargon
Short programs in some cases sink participants in citations. The evidence in prehospital pain monitoring, while advancing, sustains a couple of useful facts. Early analgesia boosts patient cooperation, which shortens extrication and boosts step-by-step success. Multimodal methods lower single-agent adverse effects. Intranasal paths are risk-free and reliable in different ages when dosed properly. Methoxyflurane supplies rapid alleviation however needs queasiness preparation. Opioid unfavorable events are uncommon with cautious titration and surveillance, however they do occur, and naloxone must be available.
The evidence additionally reminds us that paperwork conformity associates with safety and security. Medical professionals that consistently record baseline and post-dose pain ratings have a tendency to detect inadequate action previously. A course that builds those habits is not simply educating documents; it is enhancing client outcomes.

Choosing a company: what to look for
Selecting a pain monitoring qualification training course is much easier if you concentrate on a couple of concrete requirements rather than shiny brochures.
- Clear mapping to PUAEME008 Give pain monitoring, with published learning end results that match the device's components and efficiency criteria. Hands-on exercise with the specific devices and shipment paths your solution makes use of, consisting of methoxyflurane arrangements, atomisers, and spacer technique if relevant. Qualified instructors with frontline experience who can offer based responses, not just recite slides. Assessment that includes observed situations, not only multiple-choice quizzes. Ask whether you will be evaluated on a complete scenario from assessment to handover. Post-course support, such as quick-reference cards, dose calculators, and a line of call for procedure questions.
If you are seeking a discomfort administration certification to satisfy a credentialing demand, validate that the provider issues a statement of achievement that lists PUAEME008. Lots of short courses hurting monitoring offer wonderful understanding however do not honor recognised devices. That is great for specialist advancement, yet it will not satisfy HR's "discomfort management accreditation course" requirement.
How organisations can embed the gains
One-off training fades unless the work environment reinforces it. Solutions that get value from pain monitoring training programs do a couple of simple points. They stock the gear in predictable areas and sizes, from paediatric atomisers to grown-up cannulas. They include discomfort review motivates to individual treatment records. They motivate case reviews where groups talk about missed analgesia chances without blame. They build a culture where asking for a 2nd set of eyes on a complicated application concern is applauded, not punished.
A tiny instance: one center included a brilliant orange sticker label to the front of every severe injury documents that checks out "Baseline pain score videotaped?" Compliance jumped for the simple reason that the timely showed up at the best minute. Training grew the idea; the system made it stick.
An example training day that meets the standard
Providers arrange various timetables, yet a sensible single-day pathway for a PUAEME008-aligned discomfort administration training course could look like this:
- Morning online modules finished prior to participation, covering physiology of discomfort, pharmacology fundamentals, and device elements, 2 to 3 hours. Brief in-person recap and Q&A with neighborhood procedure focus, 45 minutes. Device stations rotating via methoxyflurane setting up and mentoring, intranasal distribution with dosage estimations, and documents drills, 90 minutes. Scenario block with 3 situations per student: paediatric burn, senior hip fracture, and agitated intoxicated trauma, 2 hours consisting of debriefs that concentrate on judgment and communication. Assessment situation and expertise check, 60 to 90 mins, with immediate responses and remediation time where needed. Closing conversation on handover language, unfavorable occasion acceleration plans, and integrating non-pharmacologic strategies during transportation, 30 minutes.
That cadence gives adequate rep to build muscle mass memory without fatiguing students. The assessment situation must be strenuous, with reasonable screens and time pressure, to show field demands.
Where short training courses sit within wider discomfort education
A discomfort monitoring certificate course straightened to PUAEME008 is not a fellowship suffering medication, and it needs to not claim to be. It is a concentrated credential for emergency pain management at the point of treatment. For clinicians that want to deepen abilities, paths exist: expanded extent programs that add ketamine and nitrous, sedation modules, or multidisciplinary certificate programs that connect severe and chronic discomfort. The factor is to match the training to your role. Overtraining beyond range elevates threat if your office does not support the added skills.
Physiotherapists who complete an intense care pain administration training course could next go after training in graded exposure and main sensitisation for persistent problems. Nurses in remote clinics might include a step-by-step sedation module or fracture administration to prolong their ability. The very best suppliers will encourage on those pathways, not just offer the following course.
The human side of pain relief
A last believed from the area. Years ago, after a late-night phone call to a farmhouse, we located an older male with a collarbone fracture from a fall. He waved off aid till his other half urged. He held up until the first 3 breaths of methoxyflurane, then his eyes softened. He spoke about his canine instead of his shoulder. The discomfort was still there, yet it was smaller, and that made sufficient room for us to relocate him, safeguard the sling, and drive the long gravel track without jolting him right into a panic. The treatment was simple, well within PUAEME008. The end result depended on prep work, not heroics.
That is what good discomfort management training does. It furnishes average medical professionals to supply dependable alleviation under incomplete conditions. It mixes pharmacology, communication, and systems believing right into a repeatable sequence. And it grants a discomfort administration certificate that means greater than a course code, because the method behind it is sound.
If you are assessing pain monitoring training for registered nurses, physio therapists, or combined frontline groups, ask to see the scenarios, the devices, the assessment rubric, and the statement of accomplishment. If they associate PUAEME008 Give discomfort monitoring, and the instructors can speak through the compromises without flinching, you are most likely in excellent hands.